

Every patient monitor, ventilator, and infusion pump in a hospital generates data. The question is whether that data reaches the right people at the right time, or sits trapped inside a single device. That’s the core problem behind what is medical device integration, and it’s one that directly affects clinical outcomes, documentation accuracy, and nursing workload across every department in a health system.
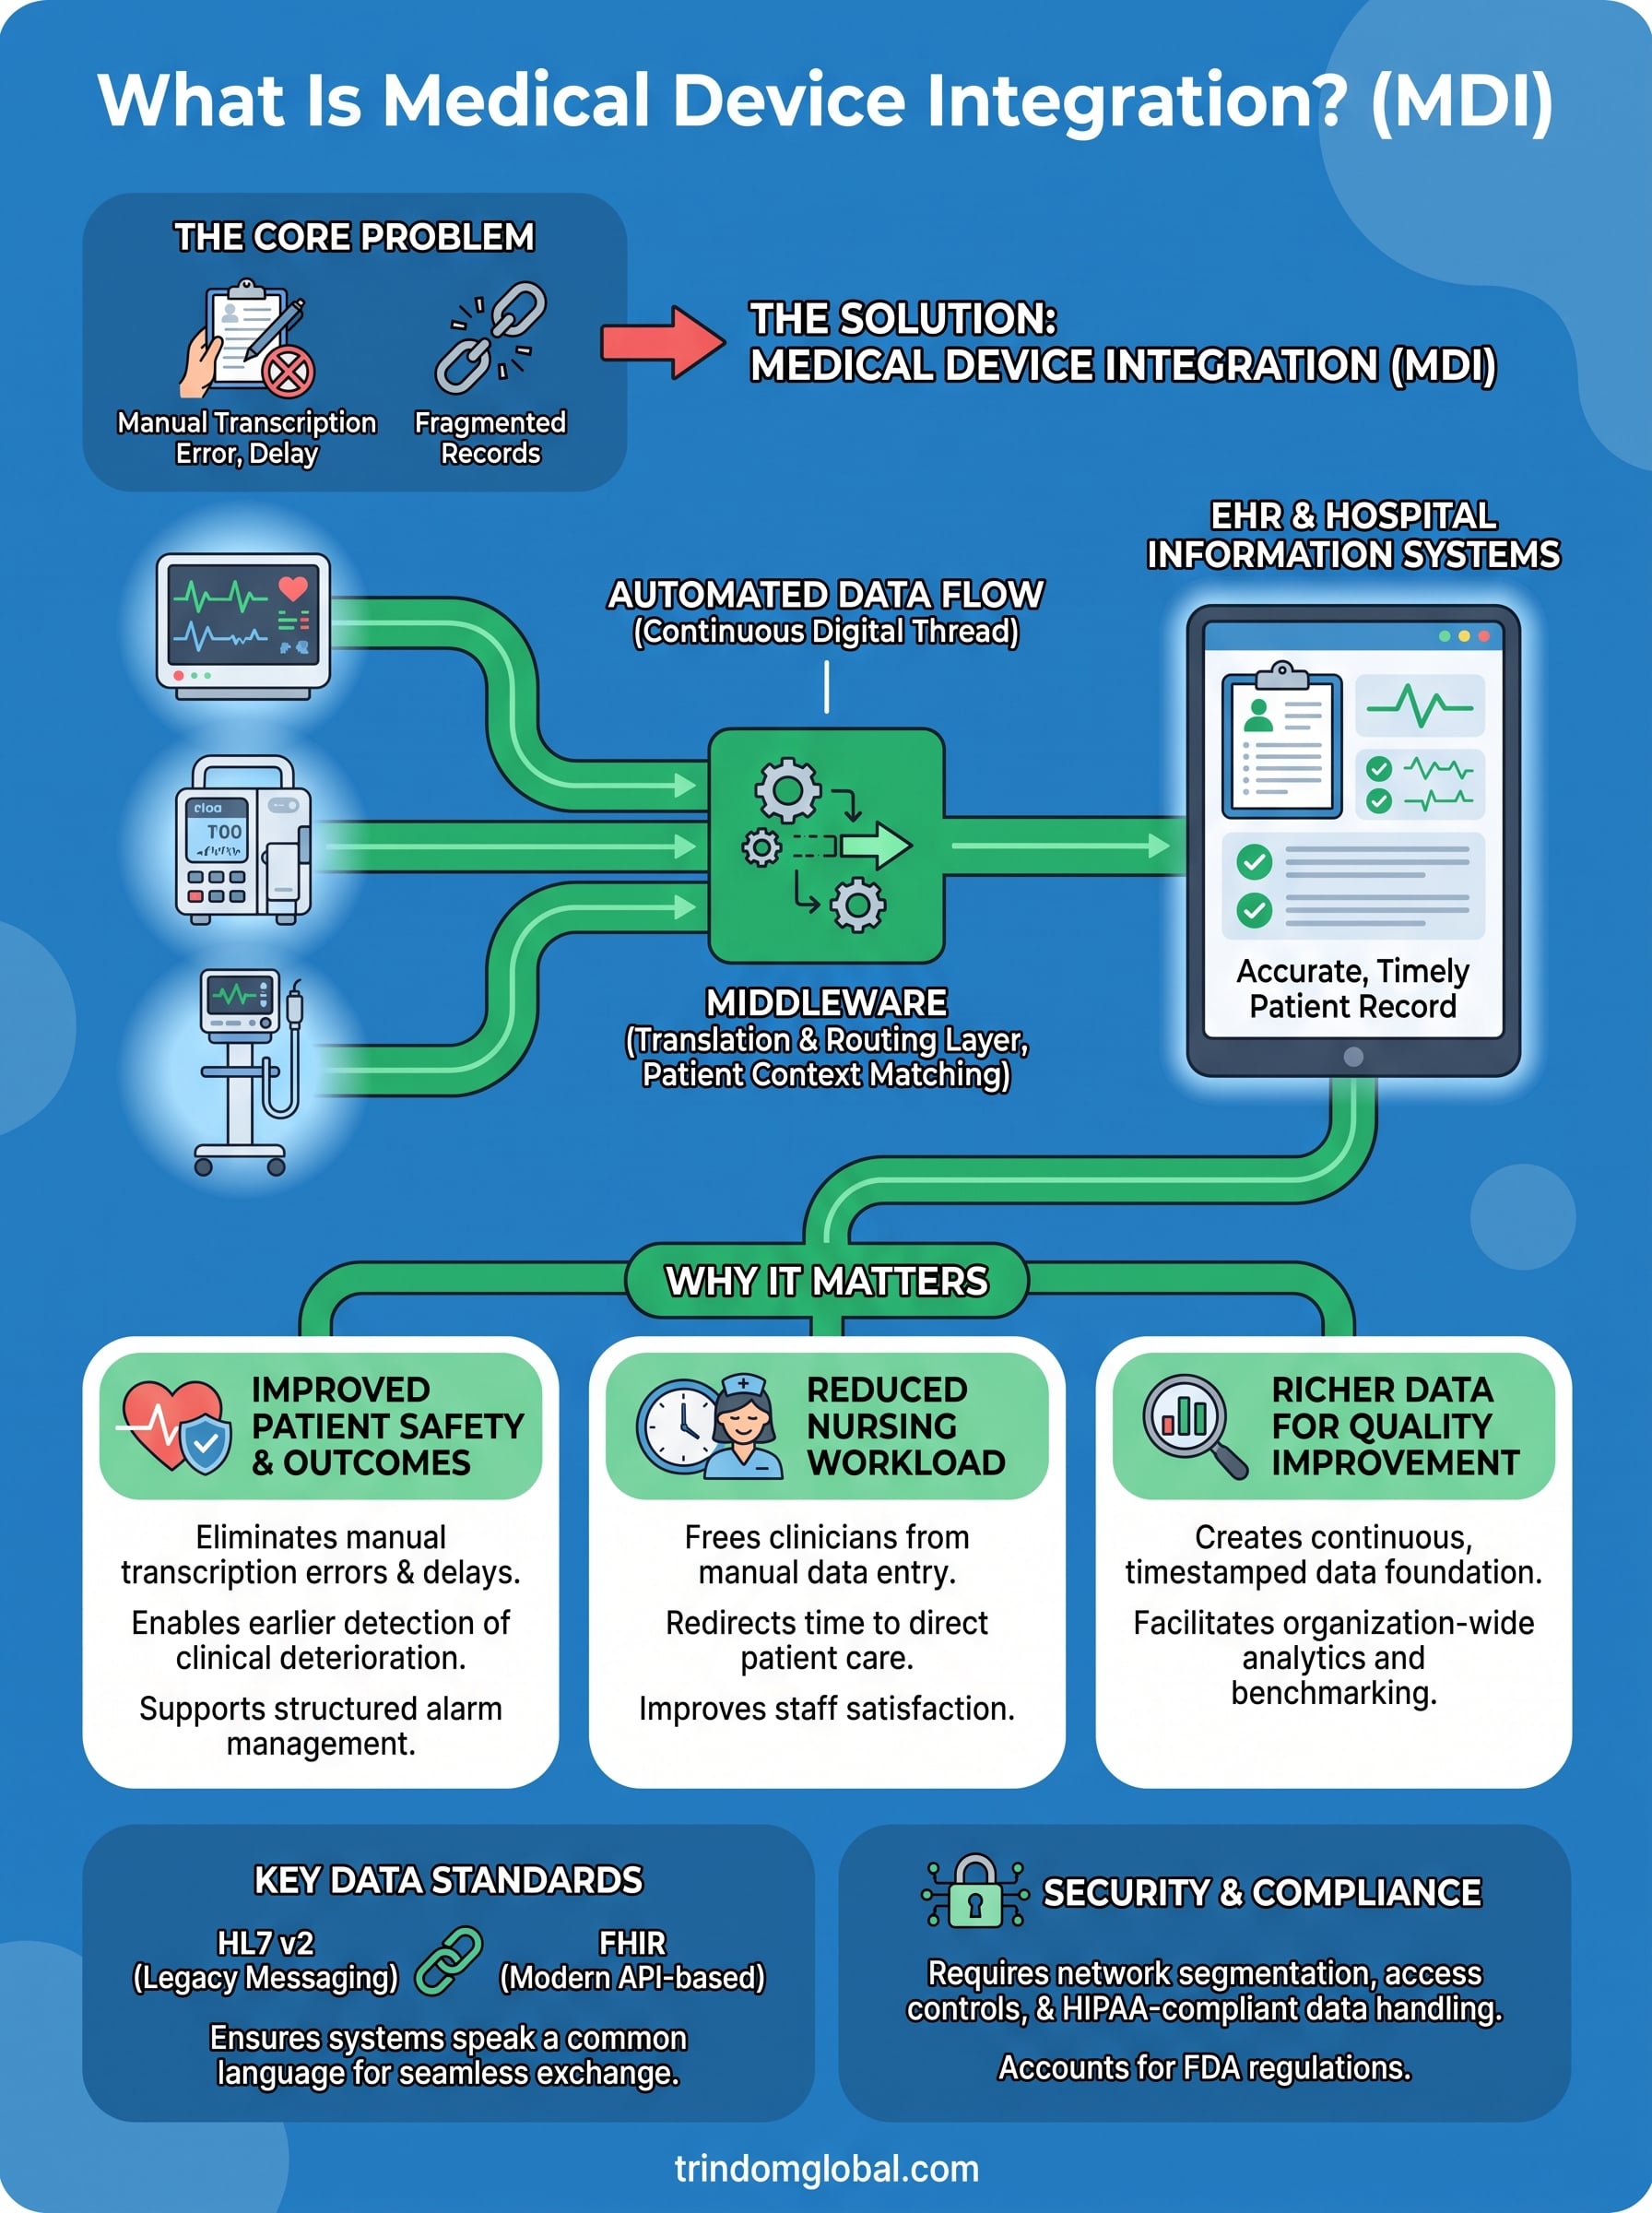
Medical device integration (MDI) is the process of connecting clinical hardware, bedside monitors, anesthesia machines, point-of-care analyzers, to electronic health records and other hospital information systems so that device-generated data flows automatically, without manual transcription. When done well, it eliminates keystroke errors, frees clinicians to focus on patients, and creates a continuous digital thread from device to chart. When done poorly, or not at all, hospitals are left with fragmented records and preventable gaps in patient safety.
At Trindom Global, we handle the infrastructure side of this equation: the structured cabling, network buildouts, and medical equipment installations that make device integration physically possible. We’ve seen firsthand how the success of any MDI initiative depends on the quality of the underlying IT backbone connecting those devices.
This article breaks down what medical device integration actually means, how it relates to interoperability standards like HL7 and FHIR, why EHR connectivity matters, and what healthcare facilities need to consider before, during, and after implementation. Whether you’re evaluating an MDI platform or planning the infrastructure to support one, this guide covers the full picture.
Why medical device integration matters in patient care
Modern hospitals generate enormous volumes of device data every hour, from vital signs captured by bedside monitors to infusion rates logged by smart pumps. Without a systematic way to move that data into the patient record, nurses and technicians spend significant time transcribing numbers by hand, a process that introduces both delay and documentation error at precisely the moments when accuracy matters most. Understanding what is medical device integration starts with recognizing that the problem is not just technical; it is a direct patient safety issue with measurable consequences in every department that relies on clinical devices.
The cost of manual data entry in clinical settings
Manual transcription is one of the most common sources of documentation errors in hospitals. When a nurse copies a blood pressure reading from a monitor to a paper log before entering it into an EHR, each step is an opportunity for a digit to be transposed, a time stamp to be wrong, or a value to be skipped entirely under time pressure. Research consistently shows that manual data entry error rates in clinical environments are high enough to affect treatment decisions, particularly in ICUs and emergency departments where device-generated data flows continuously and the volume of values to record is at its peak.
Removing manual transcription from clinical workflows does not just save time; it eliminates an entire category of preventable error from patient care.
The workload impact compounds the safety risk. Nursing time spent on documentation consistently ranks among the largest non-direct-care burdens in hospital operations. When devices connect directly with the EHR and push data automatically, clinicians reclaim that time and redirect it toward the patient in the bed rather than the clipboard on the wall. For hospitals managing tight staffing ratios, this shift carries real operational value on top of the safety benefit, and it becomes a factor in both staff retention and patient satisfaction scores.
How connected devices improve clinical outcomes
When device data flows automatically into the patient record, care teams gain a continuous, timestamped picture of patient status across a shift or an entire stay. That picture supports earlier detection of clinical deterioration, more accurate medication dosing based on real-time weight and vitals, and cleaner handoff communication between oncoming and outgoing teams. The downstream effect on outcomes, including reduced adverse events and shorter lengths of stay, appears consistently across health system quality research.

Connected devices also enable structured alarm management, where the EHR and monitoring system work together to filter low-priority alerts and escalate clinically significant ones through the right channels. Alarm fatigue is a well-documented patient safety problem in hospitals, and device integration gives clinical engineering and informatics teams a technical pathway to address it systematically, rather than relying on individual staff to make real-time judgment calls under pressure and distraction.
Your facility also builds a richer data foundation for quality improvement work. When your team can pull device-generated measurements alongside documented clinical interventions from a single, consistent source, your quality and analytics teams can identify performance patterns, benchmark against targets, and respond to adverse trends far faster than they could with data scattered across disconnected systems and paper logs. That analytical capability compounds over time, turning each integrated device into a contributor to organization-wide learning rather than an isolated data silo.
Medical device integration vs interoperability
These two terms appear together so often that healthcare teams frequently treat them as synonyms. They are not. Understanding the distinction matters when you are evaluating technology investments, responding to regulatory requirements, or planning an infrastructure upgrade for your facility. When you understand what is medical device integration and where interoperability sits alongside it, you make better decisions about both.
What interoperability actually means
Interoperability is the broader concept: the ability of different systems, devices, and software applications to exchange information and use that information effectively. It describes a spectrum, not a binary state. A device might be able to send data to one specific system but not to another, which makes it partially interoperable. Full interoperability means that any compliant system can receive, interpret, and act on data from any compliant device without custom engineering work for each connection.

Medical device integration is a specific implementation of interoperability. It refers to the actual technical work of connecting clinical hardware to hospital information systems, configuring the data flows, mapping device outputs to standard fields in the EHR, and validating that the connection performs reliably in a live clinical environment. Integration is how you achieve interoperability in practice, and it requires real infrastructure, real protocols, and real testing before you put it in front of patients.
Interoperability sets the standard; integration is the work that meets it.
Why both terms matter for your facility
Your procurement team needs to ask about interoperability when evaluating any new device or platform, because a device that cannot communicate with your existing systems will require significant additional effort and cost to integrate. At the same time, your clinical engineering and IT teams need to understand integration requirements, because interoperability certifications from a manufacturer do not guarantee a smooth deployment in your specific environment. Vendor documentation may indicate that a device supports a particular standard, but your facility’s network topology, middleware layer, and EHR version all influence whether that device actually performs the way the spec sheet describes. Knowing both concepts gives your team the language to ask the right questions at every stage of a project, from initial vendor selection through go-live validation and ongoing maintenance.
How medical device integration connects devices to EHRs
The physical connection between a bedside device and an EHR almost never happens directly. Most clinical devices speak proprietary protocols that EHR platforms cannot natively interpret, so the data pathway typically runs through an intermediary layer that translates, validates, and routes the output before it touches the patient record. Understanding this architecture is essential when you are evaluating what is medical device integration for your facility, because the reliability of the entire connection depends on every component in that chain working correctly.
Middleware as the translation layer
Middleware is the software platform that sits between your clinical devices and your EHR. It receives raw output from the device, whether that is a waveform, a discrete vital sign value, or an infusion rate, and converts it into a structured message format that your EHR can accept and file against the correct patient encounter. Without middleware, each device-to-EHR connection would require custom engineering at both endpoints, which is technically impractical and operationally unsustainable when your facility runs dozens of device types across multiple departments.

The middleware layer is where integration either succeeds or breaks down, so its configuration and maintenance deserve as much attention as the devices themselves.
Your middleware platform also handles patient context matching, which is the process of confirming that data arriving from a device is attributed to the correct patient record in the EHR. This matching typically relies on identifiers like admission number or bed assignment, and your clinical informatics team needs to validate those mappings carefully before go-live to prevent data from landing in the wrong chart.
Mapping device outputs to EHR fields
Once middleware packages the data into a standard message format, it needs to land in the correct field within the EHR flowsheet. This mapping process requires your clinical, IT, and implementation teams to agree on exactly where each device value belongs in the chart, what units the EHR expects, and how frequently the system should push updates. Devices that measure continuously, such as cardiac monitors or ventilators, generate far more data points per hour than a flowsheet can reasonably display, so your team also needs to define polling intervals and data summarization rules that keep the record useful without overwhelming it.
Thorough field mapping before deployment saves significant rework after go-live and keeps the clinical record clean enough to support both patient care and downstream quality reporting.
Common medical device integration architectures
When healthcare teams ask what is medical device integration in practice, the answer depends heavily on the architectural model a facility uses to connect devices to its information systems. No single architecture fits every environment, and your choice of model affects scalability, maintenance overhead, and how easily you can add new devices in the future. Understanding the three primary models gives your clinical engineering, IT, and infrastructure teams a clear framework for evaluating your current setup and planning for growth.
Point-to-point connections
Point-to-point architecture is the most straightforward model: a direct link between a single device and a single destination system, built with a custom interface for that specific pairing. Smaller facilities sometimes start here because it requires no middleware platform and carries lower upfront cost. The limitation becomes clear quickly. When your device count grows, each new device requires its own custom interface, and the total number of interfaces scales exponentially with every addition, creating a maintenance burden that clinical engineering teams struggle to manage without dedicated resources.
Middleware hub-and-spoke
The middleware hub-and-spoke model addresses the scaling problem by placing a central integration engine between all your devices and all your destination systems. Devices send data to the hub, the hub translates and routes it, and your EHR receives a clean, standardized message. This is the most common architecture in mid-sized and large hospital systems today because it reduces the number of point connections your team has to maintain and gives you a single platform to monitor, update, and troubleshoot when something goes wrong.
A well-configured middleware hub simplifies every future device addition, because you build one connection to the hub rather than one connection to every downstream system.
API-based and cloud-connected architectures
Newer integration platforms rely on application programming interfaces (APIs) and, in some cases, cloud-based processing to move device data into EHRs and analytics systems. This model aligns with modern EHR platforms that support FHIR-based APIs and gives your facility a more flexible foundation for scaling integration across multiple campuses or supporting remote patient monitoring programs. The tradeoff is that API-based architectures require stronger network security controls and more rigorous validation work before go-live, particularly when data leaves your on-premises environment and passes through external infrastructure. Your IT and clinical informatics teams need to align on access controls and data governance before you commit to this path.
Data standards that make integration work
Every successful integration project depends on shared data standards that allow devices, middleware, and EHR systems to communicate in a language all parties understand. When you research what is medical device integration, you will quickly find that the technical standards governing how data is formatted and transmitted matter as much as the physical connections and middleware platforms that carry it. Without agreed-upon standards, every device-to-system connection becomes a custom engineering project with its own syntax and translation rules.
HL7 and its role in clinical messaging
Health Level Seven International (HL7) is the organization that produced the original messaging standard most hospitals still rely on today: HL7 v2. This standard defines how clinical messages, including admission notifications, lab results, vital sign observations, and medication orders, are structured and transmitted between systems. Most middleware platforms speak HL7 v2 natively, and most EHRs accept it, which is why it remains the backbone of device-to-EHR communication in legacy and mid-sized hospital environments even as newer standards emerge.
HL7 v2 is effective but limited by design. It was built for a point-to-point world where predefined message types handle predictable transactions, and it lacks the flexibility modern cloud-based architectures require. Your clinical informatics team still needs to configure segment-level mappings for each message type, which takes time and requires careful validation before you trust the output in the patient record.
FHIR and modern API-based exchange
Fast Healthcare Interoperability Resources (FHIR) is the current standard from HL7 that replaces the rigid message structure of v2 with a modular, resource-based model built for modern web APIs. FHIR lets systems request and deliver specific data elements over standard HTTP connections, which makes it far easier to integrate devices with cloud platforms, patient portals, and analytics tools alongside your primary EHR.
FHIR is not a replacement you implement overnight, but committing to it now positions your facility to support the next generation of connected device programs without rebuilding your integration layer from scratch.
Your facility’s readiness for FHIR depends on whether your EHR vendor exposes FHIR-compliant APIs and whether your middleware platform can translate device output into structured FHIR resources. Both conditions are increasingly common, but your team should verify version support and available resource types before committing to an API-first architecture.
Typical use cases and benefits in hospitals and clinics
One way to make what is medical device integration concrete is to look at where hospitals and clinics actually deploy it and what changes once the connections go live. The use cases span nearly every clinical department, but the environments that see the most immediate impact are those where continuous device data drives real-time treatment decisions and where documentation volume is high enough that manual transcription creates measurable bottlenecks for every shift.
ICU and critical care monitoring
Intensive care units generate more device-driven data per patient per hour than almost any other department in a hospital. Bedside monitors, mechanical ventilators, infusion pumps, and temperature management systems all run simultaneously for each patient, and the care team needs accurate, current values available in the EHR at all times to make safe treatment decisions. When those devices connect directly to the record, nurses stop toggling between the device screen and the documentation system, and the chart reflects what the patient is actually experiencing right now rather than what was recorded during the last manual entry cycle.
Continuous, automated vital sign documentation in the ICU removes the time gap between when a value changes and when the care team can see it in the patient record.
Connected devices in critical care also support structured alarm management programs, giving clinical engineering teams a data foundation to analyze alarm frequency, adjust threshold settings based on real patient populations, and reduce the alert burden on bedside nurses without compromising safety.
Perioperative and anesthesia environments
Operating rooms and post-anesthesia care units rely on a dense cluster of devices, including anesthesia machines, hemodynamic monitors, infusion systems, and warming units, and the clinical record needs to capture output from all of them throughout a procedure. Integration allows the anesthesia information management system to pull device values automatically and build a continuous intraoperative record without requiring the anesthesiologist to manually log each measurement during an active case.
Your perioperative team also benefits on the back end. Clean, device-sourced documentation flows directly into billing and coding workflows, reducing the manual reconciliation work that post-procedure billing requires. Facilities with integrated OR environments consistently report fewer documentation discrepancies between the clinical record and the charge capture system, which translates to faster reimbursement and lower audit risk.
Security and privacy for connected medical devices
When you connect clinical devices to your hospital network and EHR, you expand the attack surface that your IT and security teams need to defend. Understanding what is medical device integration also means understanding the security obligations that come with it, because a connected device is not just a clinical tool but also a network endpoint that carries patient data and, in some cases, has direct influence over treatment delivery. Facilities that treat security as an afterthought during integration projects consistently face higher remediation costs and greater regulatory exposure than those that build security controls into the architecture from the start.
Network segmentation and access controls
Network segmentation is the most effective baseline control for protecting connected medical devices. When your clinical device network sits on a dedicated segment, isolated from general staff workstations, guest Wi-Fi, and administrative systems, a compromise in one area of your environment cannot easily spread to the devices monitoring your patients. Your IT team should apply strict access control lists at the segment boundary so that only authorized systems, such as your middleware platform and EHR, can initiate or receive connections from device endpoints.
Treating your clinical device network as a separate security zone is not optional when those devices carry patient data and influence care decisions.
Device-level authentication matters alongside segmentation. Many legacy clinical devices ship with default credentials and open ports that your security team needs to audit and lock down before the device goes live on your network. Work with your clinical engineering team to maintain an accurate device inventory, including firmware versions and known vulnerabilities, so your security posture reflects the actual environment rather than an outdated asset list.
Patient data privacy and compliance
Every data point that travels from a clinical device to your EHR is protected health information (PHI) under HIPAA, and your integration architecture needs to enforce encryption in transit and at rest for every leg of that journey. Your business associate agreements with middleware vendors and integration platform providers must address how they handle, store, and transmit that data before you allow them to touch live patient records.
Your privacy team should also review data retention policies for device-generated values stored in your middleware layer, because data that sits in a staging environment longer than necessary creates unnecessary exposure without adding clinical value to the patient record.
Safety, risk, and regulatory expectations in the US
Any facility working through what is medical device integration also needs to account for the regulatory framework that governs connected clinical devices in the United States. The Food and Drug Administration (FDA) has expanded its oversight of software and connectivity features embedded in medical devices, and that expansion directly affects how your clinical engineering, IT, and compliance teams approach integration projects. Ignoring these expectations during planning creates risk that surfaces during inspections, audits, or adverse event reviews when your facility is least prepared to address it.
FDA oversight of software and connected device functions
The FDA regulates software that functions as a medical device, and it has issued guidance clarifying that software used to acquire, process, or display data from clinical devices may itself fall within the agency’s regulatory scope. Your integration middleware may qualify as a medical device accessory depending on how it processes and routes clinical data, so your compliance team should review the FDA’s current guidance on Software as a Medical Device (SaMD) before finalizing your architecture.
Treating your middleware platform as a pure IT tool without evaluating its regulatory classification is a gap that FDA reviewers and accreditors have flagged at facilities during on-site assessments.
The FDA also requires device manufacturers to submit premarket documentation that includes cybersecurity controls for any connected device seeking clearance. Your procurement team should request that documentation when evaluating new devices, because it gives you a baseline understanding of what security controls the manufacturer built in and where your facility needs to supplement them.
Risk classification and your facility’s responsibilities
The FDA assigns medical devices to one of three risk classes based on the level of risk they pose to patients, and that classification influences how strictly the agency regulates changes to the device, including changes to its software and connectivity features. Class II and Class III devices, which include most monitoring and therapeutic equipment, carry stricter controls, and modifications to how those devices communicate with your systems may require manufacturer notification or regulatory submission depending on the nature of the change.
Your clinical engineering team needs a clear process for evaluating any integration-related change to a regulated device against its original 510(k) clearance or PMA approval. Connecting a device to your network or EHR in a way that the manufacturer did not validate as part of the original submission can shift liability to your facility if that configuration contributes to a patient safety event.
How to plan and implement medical device integration
Planning an MDI project without a clear sequence of steps leads to costly rework after go-live, and your clinical, IT, and infrastructure teams all need to operate from the same roadmap. Whether your facility is deploying integration for the first time or expanding an existing program, the planning process follows a consistent pattern: assess what you have, define what you need, build and configure it, and validate it before any connected device touches live patient data. Understanding what is medical device integration in your specific environment means mapping that process to your actual device inventory, network topology, and EHR platform rather than following a generic vendor checklist.
Start with an infrastructure and device audit
Before you configure a single interface, your clinical engineering and IT teams need a complete, current inventory of every device you plan to integrate, including manufacturer, model, firmware version, and the communication protocols each device supports. This audit reveals immediately which devices can connect through standard middleware interfaces and which ones require custom driver development or manufacturer engagement before they are ready for integration.
Your infrastructure audit should cover network cabling, port capacity, and wireless coverage in every area where integrated devices will operate, because gaps in the physical layer surface as reliability problems after go-live rather than before.
Your network team should also assess bandwidth and latency across your clinical device segments during this phase, because continuous data streams from monitoring equipment add real load to your infrastructure, especially in high-density areas like ICUs and operating rooms.
Define your data governance and workflow requirements
Your clinical informatics and nursing informatics teams need to define exactly which device values belong in the EHR, at what polling frequency, and in which flowsheet fields, before your implementation team touches a configuration file. These decisions belong to clinical leadership, not IT, because the people closest to patient care understand what data supports decision-making versus what creates noise in the chart.
Documenting these requirements in a formal data mapping specification before build work begins gives your implementation team clear acceptance criteria and gives your compliance team a record that supports regulatory review.
Validate before you go live
Your validation phase needs to include end-to-end testing in a non-production environment that mirrors your live EHR and middleware configuration as closely as possible. Test each device type, each message format, and each patient matching scenario your team identified during the workflow design phase, then have clinical staff review the results against their documentation expectations before you approve the connection for production use.
A simple wrap-up
Medical device integration is the technical and operational process of connecting clinical hardware to your EHR and hospital information systems so that device-generated data flows automatically, without manual transcription, into the patient record. When you understand what is medical device integration at every layer, from data standards and middleware architecture to network security and regulatory requirements, you give your facility a clearer path to safer, more efficient care delivery.
Every component covered in this article, from HL7 and FHIR standards to FDA risk classification and infrastructure validation, connects back to the same goal: accurate, reliable data in the hands of your care team when they need it. The physical infrastructure supporting those connections matters as much as the software. If you need a partner to handle the installation and network buildout side of that equation, Trindom Global’s medical equipment installation services are built for exactly that work.


